 Auscultify
Every heart murmur on Step 1, and how to hear it in the audio questions
Step 1 tests murmurs two ways: vignettes that describe a sound and expect you to name the lesion, and multimedia items that play the sound and expect you to recognize it. Most students prepare for the first and get ambushed by the second. This page covers both.
Free to download · Pro includes a 7-day free trial · Cancel anytime
The Step 1 murmur table
Timing, location, radiation, character and the one association the exam loves. Learn the rows, then learn to hear them.
| Lesion | Timing | Best heard | Radiates / character | Classic Step 1 association |
|---|---|---|---|---|
| Aortic stenosis | Systolic, crescendo-decrescendo | Right 2nd ICS | Carotids; soft or paradoxically split S2, pulsus parvus et tardus | Elderly calcific, bicuspid valve in the young, syncope-angina-dyspnea |
| Mitral regurgitation | Holosystolic, blowing | Apex | Axilla; louder with squatting and handgrip | Post-MI papillary muscle rupture, rheumatic, MVP progression |
| Mitral valve prolapse | Mid-systolic click, late systolic murmur | Apex | Click earlier with standing and Valsalva, later with squatting | Young woman, myxomatous degeneration, connective tissue disease |
| Tricuspid regurgitation | Holosystolic | Lower left sternal border | Louder with inspiration (Carvallo) | IV drug use endocarditis, pulmonary hypertension |
| Ventricular septal defect | Holosystolic, harsh | Lower left sternal border | Louder with handgrip; smaller defect, louder murmur | Most common congenital heart defect |
| Aortic regurgitation | Early diastolic, decrescendo, blowing | Left sternal border, leaning forward, end-expiration | Wide pulse pressure, head bobbing, water-hammer pulse; Austin Flint rumble | Bicuspid valve, endocarditis, aortic root dilation, syphilis |
| Mitral stenosis | Mid-diastolic rumble after an opening snap | Apex, bell, left lateral | Shorter S2 to opening snap interval means more severe | Rheumatic heart disease, left atrial enlargement, AFib |
| Hypertrophic cardiomyopathy | Systolic, crescendo-decrescendo | Left sternal border | Louder with Valsalva and standing, softer with squatting; no carotid radiation | Young athlete sudden death, S4, mitral regurgitation from SAM |
| Patent ductus arteriosus | Continuous, machine-like | Left infraclavicular | Peaks at S2 | Prematurity, congenital rubella; closed with indomethacin |
| Atrial septal defect | Systolic ejection murmur with wide fixed split S2 | Pulmonic area | The fixed split is the finding | Paradoxical embolism, Down syndrome (ostium primum) |
The maneuvers Step 1 cannot stop asking about
Standing and Valsalva
Decrease preload. Almost every murmur gets softer. Two get louder: hypertrophic cardiomyopathy, and the click of MVP moves earlier and the murmur lengthens.
Squatting and leg raise
Increase preload and afterload. Most murmurs get louder. HCM gets softer; the MVP click moves later and the murmur shortens.
Handgrip
Increases afterload. Louder: mitral regurgitation, aortic regurgitation, VSD. Softer: aortic stenosis, HCM. A clean way to separate AS from HCM.
Inspiration
Right-sided murmurs get louder (tricuspid and pulmonic), left-sided get softer or stay the same. The mnemonic is RILE: right inspiration, left expiration.
Amyl nitrite
Decreases afterload. Louder: AS, HCM, MVP. Softer: MR, AR, VSD. Rare on the exam now but still appears in older-style questions.
How to remember it
Ask one question: does the maneuver put more blood in the ventricle or make it harder to push out? Then ask which lesion wants the opposite. The mnemonics guide has the rest.
The audio questions nobody prepares for
Step 1 includes multimedia items that play a heart sound through your headphones and ask you to identify it or pick the diagnosis. The exam's own tutorial includes an example so you can check your test-day setup. Many students report several such items per form.
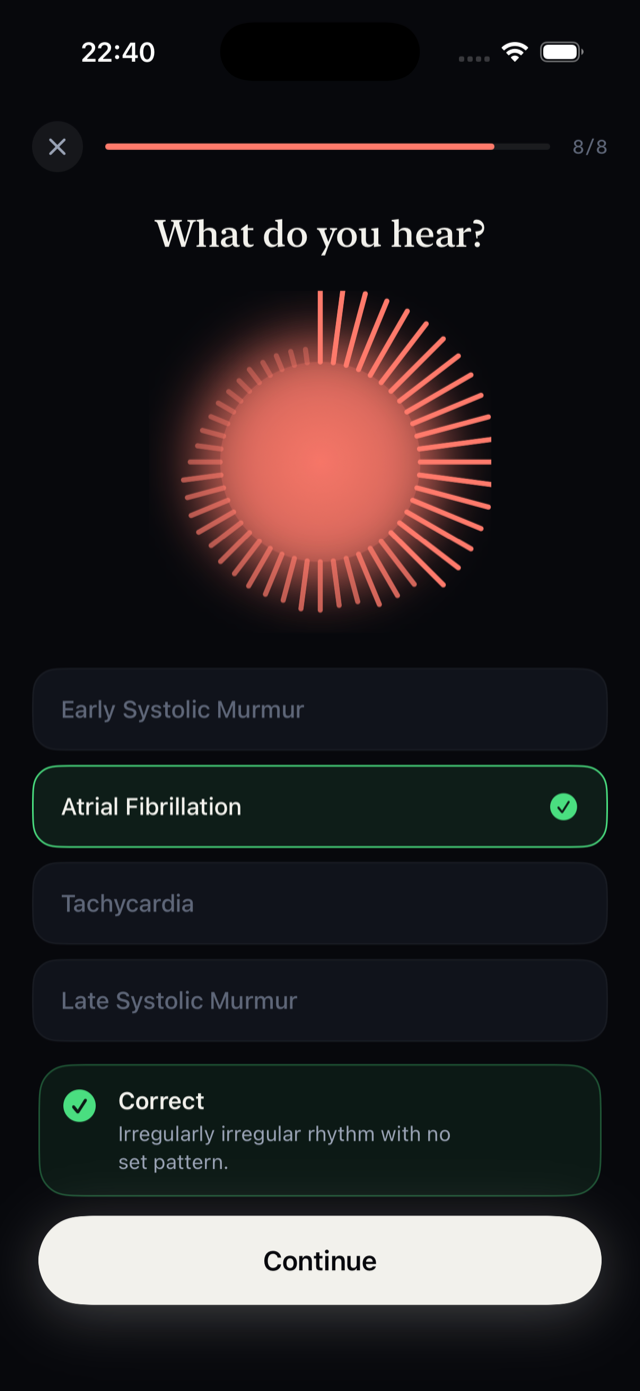
These cannot be reasoned through from a table. If you have only ever read that aortic stenosis is crescendo-decrescendo, the recording will sound like noise. If you have heard a real one fifty times, you will know it in two beats. That is the gap Auscultify closes: real patient recordings, played unlabeled, with instant feedback and spaced repetition on the ones you miss.
- Every lesion in the table above, recorded on real patients
- Heard at the site where it is loudest, the way the exam frames it
- S3, S4, opening snaps, clicks and splits alongside murmurs
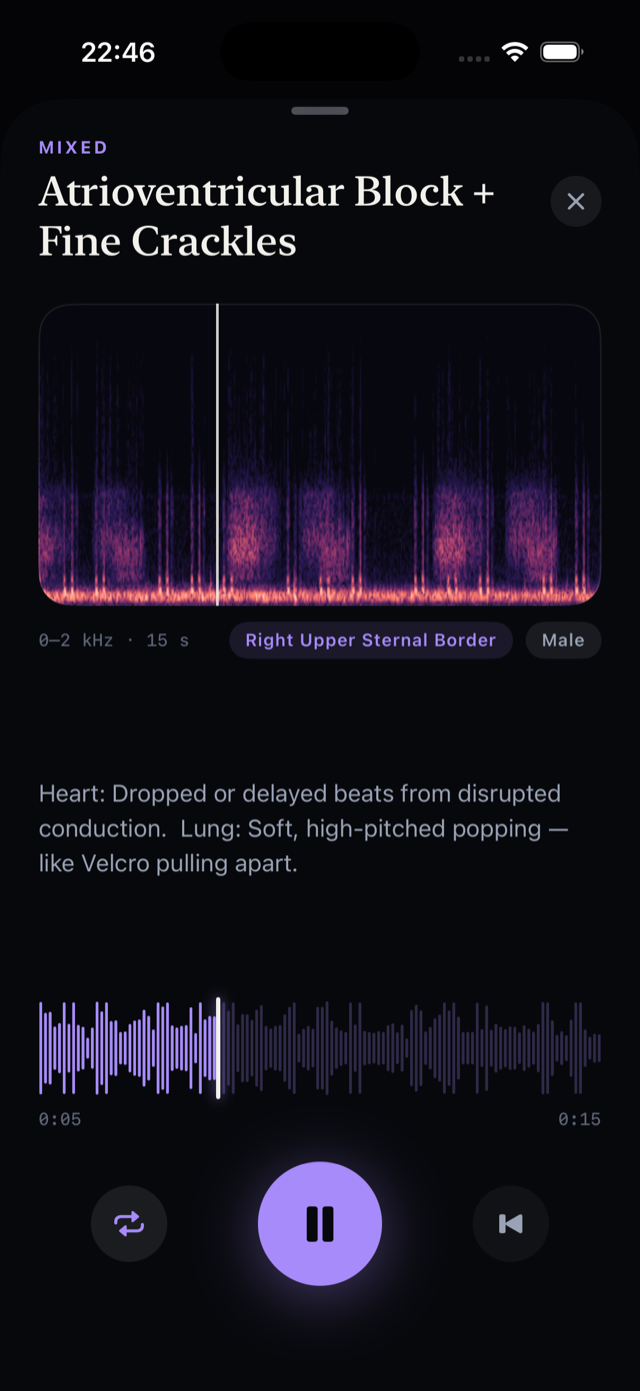
- Spectrogram view (Pro) to see the diamond, the decrescendo, the rumble
A dedicated-period plan
Week 1: table and timing
Learn the murmur table. Then 20 questions a day in Heart Sounds mode, with one goal: systolic or diastolic, every time, before anything else.
Week 2: lesion and site
40 questions a day. Name the lesion. Let the app weight your misses. Read the feedback reasoning; it is the same reasoning the vignettes use.
Week 3 onward: maintenance
10 questions a day to hold the ear through the rest of dedicated. Add Lung Sounds mode for the respiratory block. Do the clinical cases once.
Related guides
Frequently asked questions
Does USMLE Step 1 have audio heart sound questions?
Yes. Step 1 includes multimedia items that play a heart sound and ask you to identify it or choose the diagnosis. The official practice materials include an example so you can test your headphones. The number per form varies, but you should expect several.
Which murmurs are highest yield for Step 1?
Aortic stenosis, mitral regurgitation, mitral valve prolapse, aortic regurgitation, mitral stenosis, hypertrophic cardiomyopathy, VSD, tricuspid regurgitation, PDA and ASD with its fixed split S2. Know timing, site, radiation, the maneuver response and the one classic association for each.
How do I tell aortic stenosis from hypertrophic cardiomyopathy?
Both are systolic crescendo-decrescendo murmurs. AS radiates to the carotids, has a slow weak pulse and gets softer with Valsalva. HCM does not radiate to the carotids, has a brisk pulse and gets louder with Valsalva and standing because less preload worsens the outflow obstruction. Handgrip softens both but is a cleaner discriminator from MR.
What is the best way to practice murmurs for Step 1?
Learn the table, then drill real recordings unlabeled until recognition is automatic. Auscultify plays real patient murmurs, gallops and extra sounds, asks what you hear, gives instant feedback and brings back your misses. Twenty to forty questions a day for two weeks during dedicated is enough.
Is Auscultify free?
Free to download, with daily practice at no cost. Pro adds spectrogram training, decomposition, landmark drills and unlimited sessions, with a 7-day free trial. Cancel anytime.
Does the app cover Step 2 CK and shelf exams too?
Yes. The same recordings and reasoning apply to the medicine and pediatrics shelves and to Step 2 CK, where murmur vignettes shift toward management but still begin with recognizing the sound.
Know the murmur
before the stem finishes.
Real recordings, unlabeled, with spaced repetition on your misses. Free to download, Pro trial included.
Download Auscultify on the App StoreFree to download · 7-day Pro trial · Cancel anytime